

Expertise and Outcomes
University Hospital participates in Get With the Guidelines® – Stroke, a hospital-based program of the American Heart Association/American Stroke Association for improving stroke care by promoting consistent adherence to the latest scientific treatment guidelines. In 2025, for the thirteenth year in a row, University Hospital received recognition for Gold Plus Achievement for successfully meeting or exceeding research-based standards for the diagnosis and treatment of stroke patients.
To achieve “Gold Plus” recognition, a hospital must reach an aggressive goal of treating patients with 85 percent or higher in each of seven stroke achievement measures as outlined by American Heart Association/American Stroke Association for 24 months or more. In addition, the hospital must demonstrate 75 percent consistent compliance with four out of seven additional quality measures.
GWTG-Stroke’s Target: StrokeSM Honor Roll award recognizes hospitals that rapidly treat ischemic stroke patients with the critical clot-busting drug tPA (tissue plasminogen activator). Most ischemic strokes are caused by the blockage of a brain artery by a clot and tPA can be given intravenously to break up the clot and restore normal blood flow to the brain. To be effective, tPA must be administered within 4.5 hours of the onset of stroke symptoms; and the sooner it is administered, the more effective this treatment is in achieving excellent outcomes, defined as patients experiencing mild or no disability at 90 days from the stroke. Once a patient arrives in the hospital, tPA should be given within 60 minutes of arrival.
University Hospital was recognized in 2023, 2024, and 2025 with the Target: Stroke Elite Plus award for administering tPA to eligible stroke patients within 60 minutes of arrival at the hospital at least 85% of the time, within 45 minutes of arrival at least 75% of the time and within 30 minutes of arrival at least 50% of the time during a 12-month period. We consistently exceeded this target, and we increased the percentage of patients who were given tPA within 30 minutes.
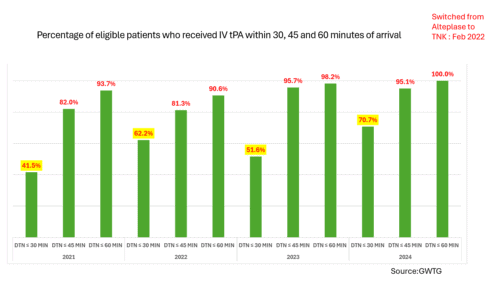
Percentage of eligible patients who received IV tPA within 30, 45 and 60 minutes of arrival (door-to-needle time, DTN).
- 2021: 41.5% within 30 minutes, 82.0% within 45 minutes, 93.7% within 60 minutes.
- 2022: 62.2%, 81.3%, 90.6%.
- 2023: 51.6%, 95.7%, 98.2%.
- 2024: 70.7%, 95.1%, 100.0%.
Switched from Alteplase to TNK in February 2022. Source: GWTG.
All data presented on this website is University Hospital’s independent analysis of data gathered using the Get With The Guidelines Patient Management Tool.TM It is not an analysis of the national Get With The Guidelines dataset and does not represent findings from the AHA Get With The Guidelines National Program.
In 2022, our average tPA administration time was 38.7 minutes. We are consistently improving our tPA administration time from the time of patient arrival to the ED and in 2024 the average tPA administration time was 34.8 minutes.

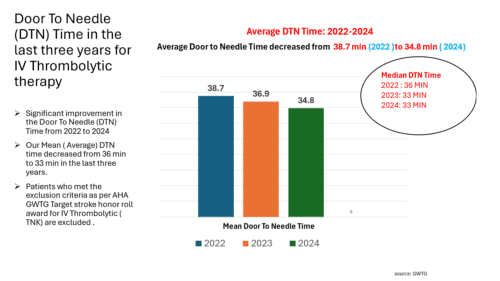
Door-to-needle (DTN) time for IV thrombolytic therapy, 2022 to 2024.
- Mean (average) DTN time: 38.7 minutes in 2022, 36.9 minutes in 2023, 34.8 minutes in 2024.
- Median DTN time: 36 minutes in 2022, 33 minutes in 2023, 33 minutes in 2024.
Patients who met the exclusion criteria of the AHA GWTG Target: Stroke Honor Roll award for IV thrombolytic (TNK) therapy are excluded. Source: GWTG.
All data presented on this website is University Hospital’s independent analysis of data gathered using the Get With The Guidelines Patient Management Tool.TM It is not an analysis of the national Get With The Guidelines dataset and does not represent findings from the AHA Get With The Guidelines National Program.
For certain patients, physical removal of the blood clot causing the stroke becomes necessary. As a Comprehensive Stroke Center, trained doctors (endovascular surgeons) are available 24/7 to thread a catheter through an artery in the groin or arm up to the blocked artery in the brain, allowing the direct, mechanical removal of the clot. This is called “mechanical reperfusion”
or “catheter-based reperfusion”. This procedure can be done for some patients up to 24 hours from the time the patient is known to be normal or at baseline function. At University Hospital we have a high success rate with mechanical reperfusion. In 2024 our specialists were able to remove the clot and re-establish substantial blood flow 90.3% of the time that mechanical endovascular reperfusion therapy was performed on eligible ischemic stroke patients.
Opening a blood vessel with intravenous tPA or by catheter-based reperfusion carries a small risk of hemorrhage with worsening of the stroke (symptomatic hemorrhage). According to the original large study which led to the approval by the FDA for the use of IV tPA for acute stroke, the symptomatic hemorrhage rate for IV tPA treatment should be less than 6.2% per year. From 2022 to 2024, our symptomatic hemorrhage rate and other complications, whether patients were treated with intravenous tPA, catheter-based reperfusion, or both, ranged from 1.9% to 5.6%.
It is critical that the public becomes familiar with the signs and symptoms of stroke, and that someone calls 9-1-1 immediately. University Hospital has extensive experience in treating stroke patients with removing clots safely. The number of catheter-based endovascular reperfusion procedures has increased over the past few years. In 2022 we treated 75 patients and in 2023 it was 84 patients. In 2024 we treated 96 patients.
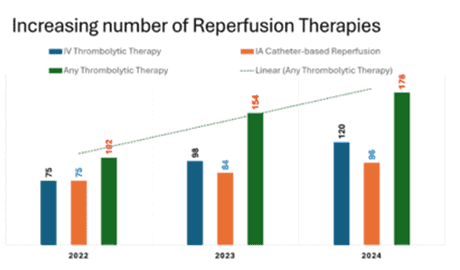
Increasing number of reperfusion therapies.
- 2022: 75 IV thrombolytic therapies, 75 IA catheter-based reperfusions, 102 patients given any thrombolytic therapy.
- 2023: 98, 84 and 154.
- 2024: 120, 96 and 178.
A trend line for “any thrombolytic therapy” rises across the three years.
All data presented on this website is University Hospital’s independent analysis of data gathered using the Get With The Guidelines Patient Management Tool.TM It is not an analysis of the national Get With The Guidelines dataset and does not represent findings from the AHA Get With The Guidelines National Program.
The percentage of patients who had a functional outcome of independence at 90 days after receiving any thrombolytic therapy improved from 30% in 2021 to 39.1% in 2024.
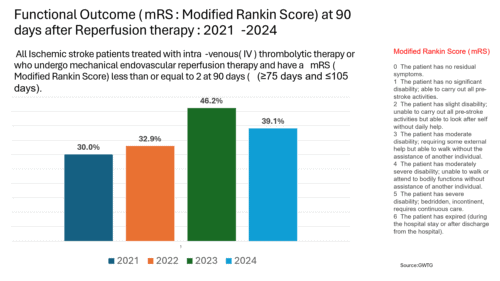
Functional outcome (mRS: Modified Rankin Score) at 90 days after reperfusion therapy, 2021 to 2024: the percentage of all ischemic stroke patients treated with IV thrombolytic therapy or mechanical endovascular reperfusion who had an mRS of 2 or less at 90 days (75 to 105 days).
- 2021: 30.0%.
- 2022: 32.9%.
- 2023: 46.2%.
- 2024: 39.1%.
The Modified Rankin Score:
- 0, no residual symptoms;
- 1, no significant disability, able to carry out all pre-stroke activities;
- 2, slight disability, unable to carry out all pre-stroke activities but able to look after self without daily help;
- 3, moderate disability, requiring some external help but able to walk without the assistance of another individual;
- 4, moderately severe disability, unable to walk or attend to bodily functions without assistance;
- 5, severe disability, bedridden, incontinent, requires continuous care;
- 6, the patient has died.
Source: GWTG.
All data presented on this website is University Hospital‘s independent analysis of data gathered using the Get With The Guidelines Patient Management Tool.TM It is not an analysis of the national Get With The Guidelines dataset and does not represent findings from the AHA Get With The Guidelines National Program.
Other Early Treatments for Stroke
University Hospital’s team of experts includes surgeons who specialize in stroke treatment. Procedures include:
- Carotid Artery surgery or stents
- Cerebral Aneurysm surgery
- Treatment of Arteriovenous Malformations (AVM)
- Surgery to relieve pressure on the brain from very large ischemic or hemorrhagic strokes
Make an appointment
150 Bergen St, Newark, NJ 07103
Operating Hours: 24 hours a day, 7 days a week